
Ebola is spreading faster – Needed international aid is way down

A man hangs an Ebola awareness banner in the Kigonze camp in Bunia, in the eastern Democratic Republic of the Congo.
Ebola is a nasty, viral disease, mainly found in Western and Central Africa. It comes in four genetically distinct types. Untreated, it has a fatality rate of 30% to 90%, but good early medical care significantly reduces these rates.
Ebola was first identified in West Africa in the 1970s, and since then there have been 17 outbreaks, killing tens of thousands of people and sickening even more. Many of these outbreaks have occurred in the eastern provinces of the Democratic Republic of the Congo (DRC).
Ebola outbreaks begin through “spillover events,” where the virus transfers from an animal host to a human. Certain animals like fruit bats are basically healthy even when they are infected with Ebola.
Human spread typically begins when a person eats infected wildlife (bushmeat) such as fruit bats or non-human primates. The outbreak then spreads from person to person through direct contact with infected bodily fluids, including blood, sweat, tears or semen.
Since big portions of the eastern DRC have had their habitat broken up by economic development, bushmeat is more available.
The most common type of Ebola is called Zaire; vaccine and monoclonal antibody therapies for it exist. The current Ebola outbreak is due to a type of Ebola called Bundibugyo, which has neither a vaccine nor officially approved therapies, although both, according to the World Health Organization (WHO), are under active development.
Lack of international aid
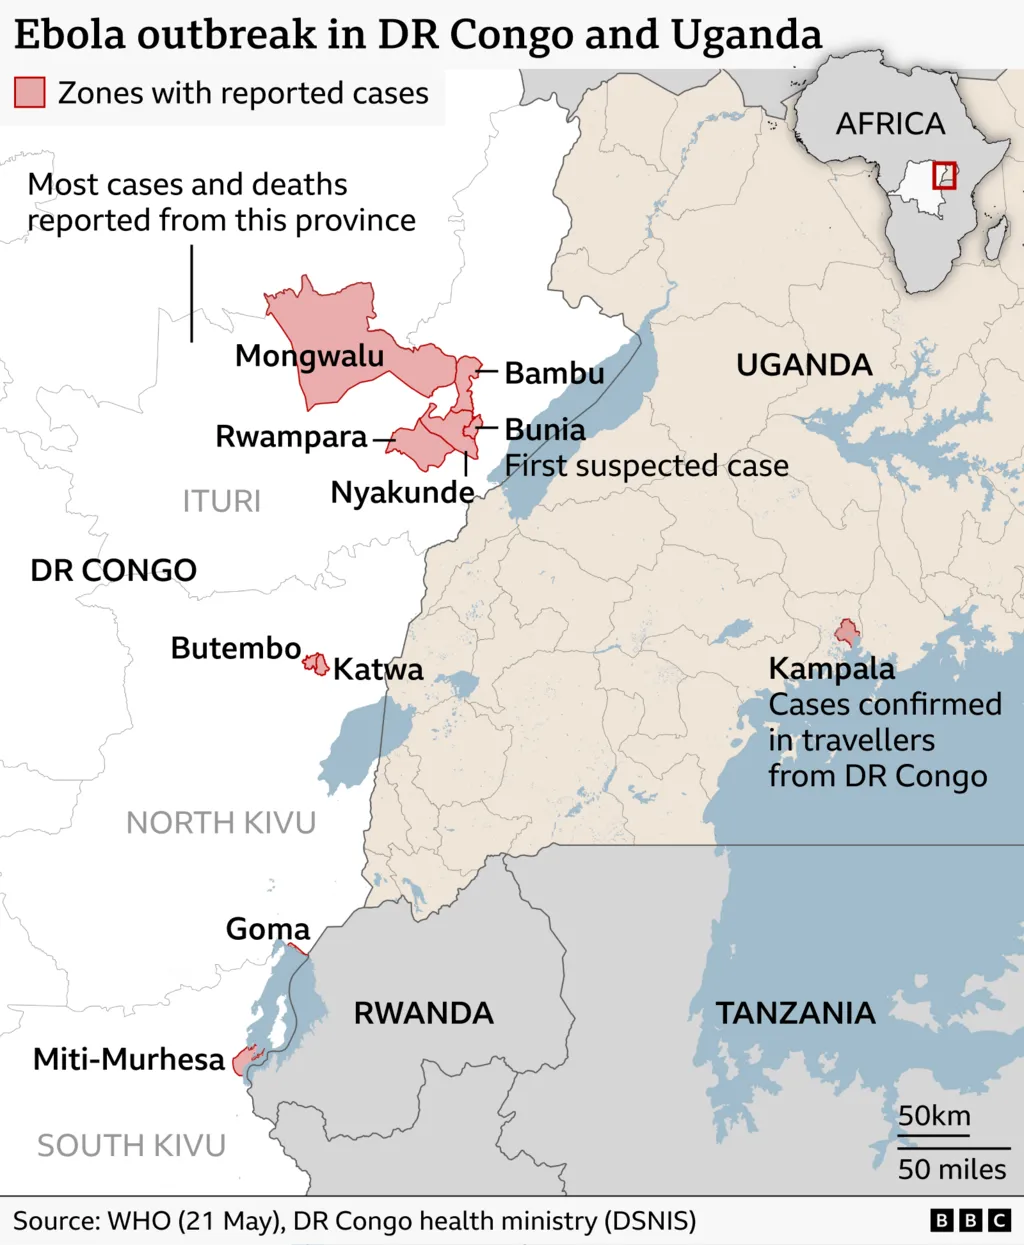
Congolese authorities say the number of confirmed cases in the DRC reached 225 on May 29, nearly double the figure of 121 reported two days earlier. Since it takes days for the tests for Ebola to be processed, this figure is just a floor; the real figure is much higher, but official numbers still indicate that Ebola is spreading rapidly. Doctors Without Borders, known by its French initials MSF, calls this one of the fastest-spreading Ebola outbreaks ever recorded.
The WHO has declared the outbreak a global health emergency, its highest level of alarm. Ebola had probably been spreading widely before the first case was established in late April, because the tests used then were designed to detect the presence of the Zaire type. A general test is more expensive.
The European Union has sent medical supplies to Ituri, the province of the DRC with the largest number of Ebola cases, and the United States has pledged more than $112 million. This amount is pathetically low given the seriousness of the crisis. The Africa Centers for Disease Control and Prevention (Africa CDC), the African Union’s health body, says global funding for the response has been cut by more than half, from $498 million for the last outbreak to $219 million for the current one.
U.S. financial aid allocated for Ebola response plummeted by roughly 99% compared to the resources deployed during the historic 2014 and 2018-2019 outbreaks.
The United States, besides denying aid to the DRC to control Ebola, has decided to close its borders to all non-citizens coming from Ebola-impacted countries, including the DRC, South Sudan and Uganda.
For U.S. citizens infected with Ebola or having been in contact with someone who is, Washington proposed to Kenya that it set up a quarantine station in that country. When this news broke in Kenya, a high court judge issued a stay order on a petition from the Katiba Institute, a Kenyan rights group. The filing warned of “grave and imminent risks” to public health. The Kenyan doctors’ union issued a 48-hour strike alert in preparation should the government proceed with the deal.
The imperialist Western countries owe massive amounts of reparations to Africa for centuries of stealing its people, labor and resources. Fully funding Ebola treatment and prevention would be a small but necessary step.
